
Ask the Evidence: How to Use AI to Get Real Answers From Our Articles

Updated: Oct 6
For busy people, or to tune in when on the move, a Google NotebookLM audio podcast is available as a story beneath.
Why a Long Article Is Not Always Enough
Anyone who has read a thorough piece on, say, LDL cholesterol targets after a heart attack, or the relationship between visceral fat and cardiovascular risk, will recognise a familiar frustration. The information is there. The studies are cited. But finding the one paragraph that answers your specific question — does this apply to me at 62 with well-controlled hypertension but no prior events? — can feel like searching a textbook index without the index. This is not a failure of the article. It is simply the nature of written prose, which moves linearly through a topic rather than responding to the person reading it.
General practitioners face a version of this problem from the other direction. A patient arrives having read something online and asks a pointed question about a trial you may not have revisited since it was published. The consulting room is not the place to spend ten minutes locating it.
The honest answer to many clinical questions is not a single sentence but a layered one: here is what the evidence says, here is how certain that evidence is, and here is where reasonable clinicians still disagree. That layered kind of answer is exactly what a structured AI interaction can provide — provided the AI is working from reliable, clearly graded source material rather than the open internet.
What the Ask the Evidence Tool Actually Is
Behind the Ask the Evidence link at the top of our longer articles is a plain text file. It is structured specifically so that an AI assistant can parse it accurately and use it as the sole basis for answering your questions.
The file contains the same content as the article, but with two additions that matter considerably. First, every significant claim is tagged with an evidence grade: established, strong, moderate, emerging, or the author's working hypothesis. This is not cosmetic. It is the difference between an AI telling you that high-sensitivity CRP predicts cardiovascular events as if this were settled doctrine, and an AI correctly telling you that the evidence is strong but that whether treating inflammation directly improves outcomes remains an active area of research. Collapsing that distinction — presenting a plausible hypothesis as established fact — is one of the ways health information causes harm.
Second, the file includes the full reference list from the article. This means that when the AI points you to a finding, it can also point you to the actual study behind it, rather than generating a plausible-sounding citation that may not exist. Anchoring the AI to a pre-verified reference list removes that risk within the scope of our articles. The file also includes a short set of instructions telling the AI to stay within the article's evidence, to flag where guidelines genuinely disagree, and to remind the reader that the information is educational rather than a substitute for clinical assessment.
How to Use It in Practice
The process takes under two minutes. Click the Ask the Evidence link at the top of the article — it copies the structured text file directly. Paste it into whichever AI assistant you use, whether that is ChatGPT, Claude, or another, followed by your specific question. Something like: based on this article, what does the evidence say about starting a statin at my age if I have no prior cardiovascular events but a family history of early heart disease? Or, as a GP: what does this article say about the threshold at which NICE recommends treatment, and where does clinical judgement still apply?
The AI will answer using the article's own evidence and reasoning. The answer is traceable — you can read the relevant section of the article yourself and check it. At the bottom of articles, a link to ChatGPT and Claude performs the copy step automatically and prepends the instruction set the AI needs, reducing the process to click and ask.
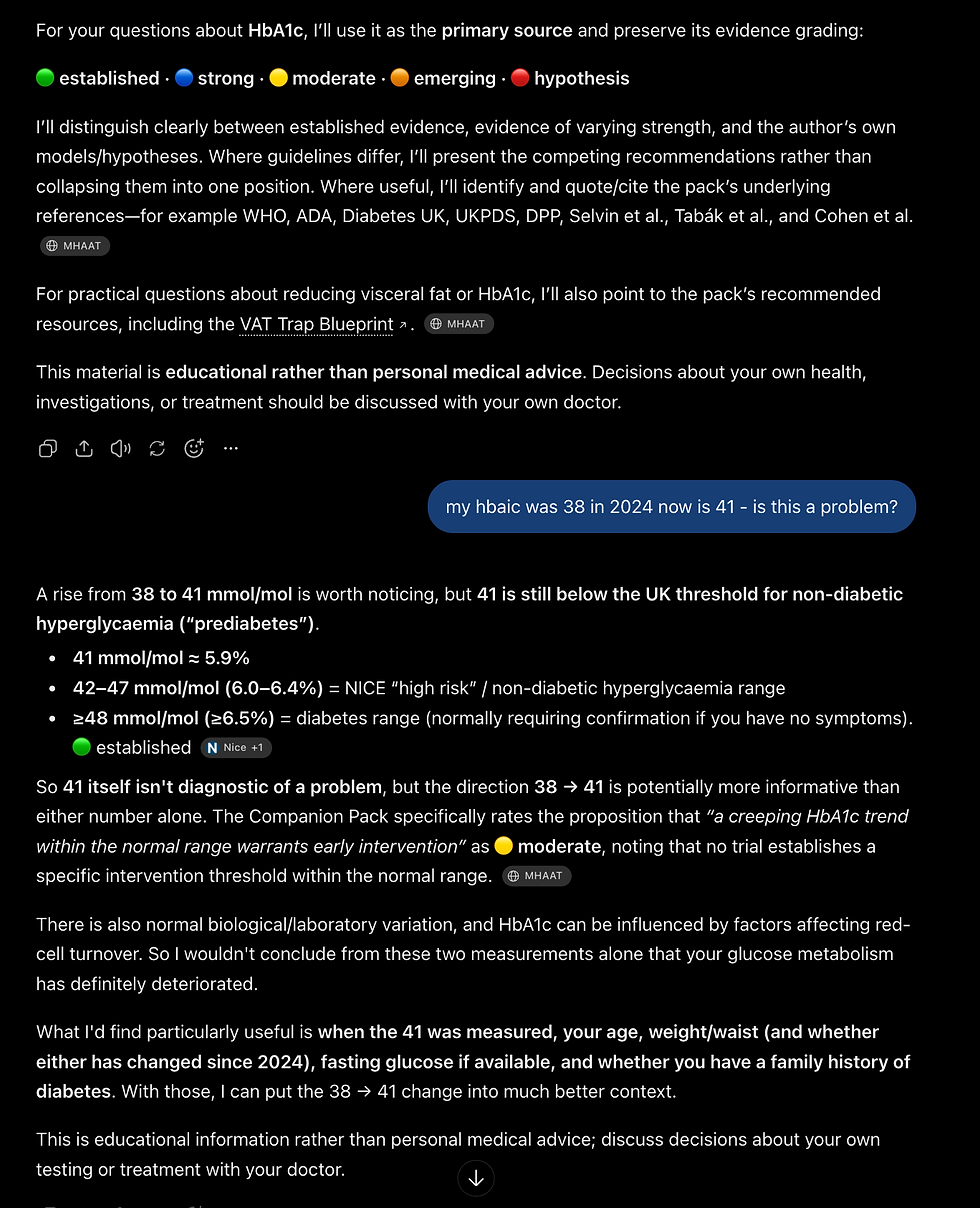
In the example shown below from a blog on HbA1c, the process is used to pose a question about my own value drifting up over a few years.
Why We Built It This Way
The straightforward answer is that we would rather you receive an answer that is traceable back to a real study than a confident-sounding response assembled from the internet at large. AI assistants are extraordinarily useful, but their default behaviour — drawing on everything they have encountered in training, blending sources of wildly varying quality, and presenting the result with uniform confidence — is not well suited to clinical information, where the difference between an established finding and an emerging hypothesis can have real consequences for a patient's decision-making.
The evidence grading system asks the AI to be transparent about certainty in the same way that a good clinician is transparent: not hedging everything into meaninglessness, but being precise about where the ground is firm and where it is not. The instruction set specifically directs the AI never to blur a hypothesis into a fact, and to flag where guidelines from different bodies — NICE, ESC, ACC/AHA — take different positions, as they sometimes do.
This is an extension of the same principle that runs through our articles themselves. Cardiovascular medicine done well is not about delivering a verdict. It is about helping a patient or a clinician understand the evidence well enough to make a genuinely informed decision. The Ask the Evidence tool is an attempt to make that possible even after the article ends and the specific, personal question begins.
Key Takeaways
1. The Ask the Evidence tool gives readers and clinicians a way to interrogate the evidence behind our articles with specific personal questions, rather than searching prose for a single relevant paragraph. 2. Every claim in the structured evidence file is graded by strength of evidence, which prevents AI assistants from presenting an emerging hypothesis with the same confidence as an established finding — a distinction that matters in clinical decision-making. 3. The full reference list is embedded in the file so that any study the AI cites can be traced back to a real, verifiable source rather than a generated citation. 4. The tool does not replace clinical assessment, and the instruction set accompanying each file explicitly reminds the AI to say so — its purpose is to make educational information more accessible and more precisely answerable, not to substitute for a consultation. 5. © Medicalspace Ltd · Surrey Cardiovascular Clinic · scvc.co.uk 2. Our longer cardiovascular articles now carry a structured evidence file readable by AI assistants like ChatGPT or Claude. Ask your specific question, get an answer tied to real studies. This piece explains how the tool works, why evidence grading matters, and how to use it in under two minutes. |
Related Blog Articles
1. ChatGPT Says My Thyroid Might Be Underactive… What Next?
2. Cardiometabolic Health Tools
3. The Four Pillars: A Temple for Your Healthspan
4. N-of-1: Why Your Best Health Plan Starts With You


